
Postpartum Engorgement: Why it Happens and How to Get Relief

Your milk volume is increasing, but your breasts feel so full and tight that feeding has become harder instead of easier. Your baby may struggle to latch onto tissue that felt soft just yesterday, and you may be wondering how to get some relief.
Engorgement can feel miserable, especially when you’re recovering from birth and already short on sleep. You haven’t done something wrong. Understanding where that pressure comes from can help you make feeding more comfortable for both you and your baby.
What is Engorgement?
Engorgement is uncomfortable fullness and swelling in your breast or chest tissue. Your breasts may feel heavy, tight, tender, or even rock hard. Early postpartum engorgement usually affects both breasts, often around days three to five after birth, although the timing can vary.
Your breasts have already been making colostrum during pregnancy. After birth, milk production increases—the change often called your milk “coming in.”
Milk collects in the tiny milk-making sacs, called alveoli, before traveling through ducts toward your nipple.
In the first days after birth, milk volume can increase quickly while your breasts are also experiencing increased blood flow and extra swelling in the tissue surrounding those sacs.
The increased blood supply supports milk production by bringing water, oxygen, and nutrients to the milk-making tissue.
Together, increasing milk volume inside the sacs and swelling in the surrounding tissue can create a perfect storm of fullness, tightness, and discomfort.
The three pictures below show how milk volume increases and how fluid in the surrounding tissue can add to the fullness. The milk inside the sacs and the fluid outside them are in different spaces.
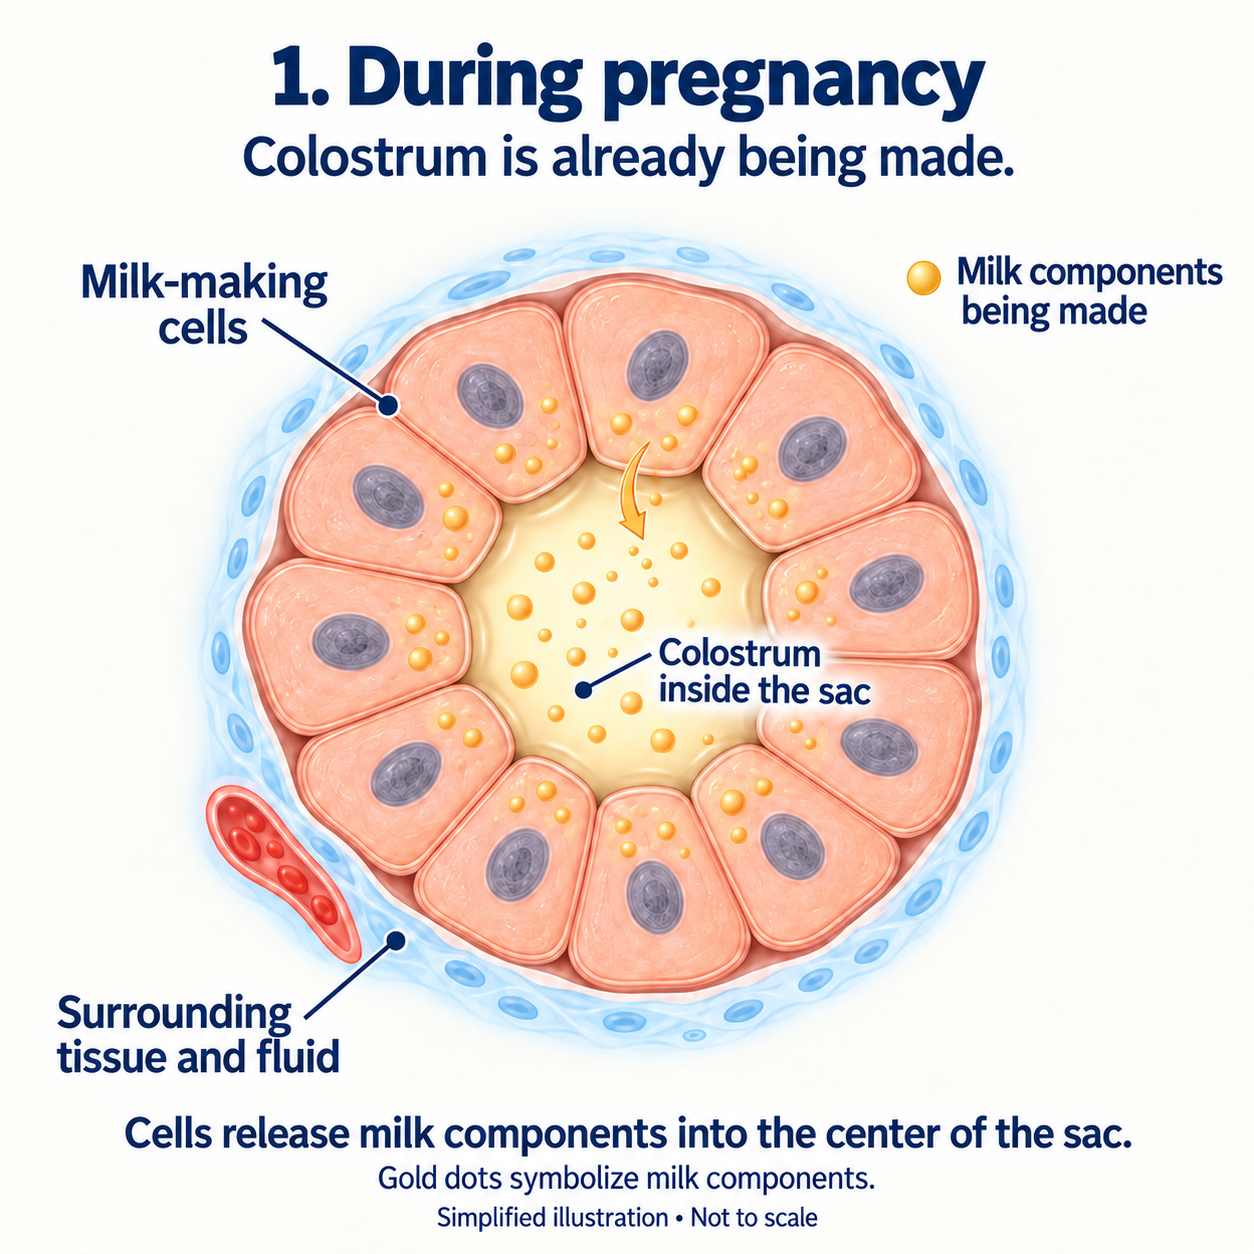
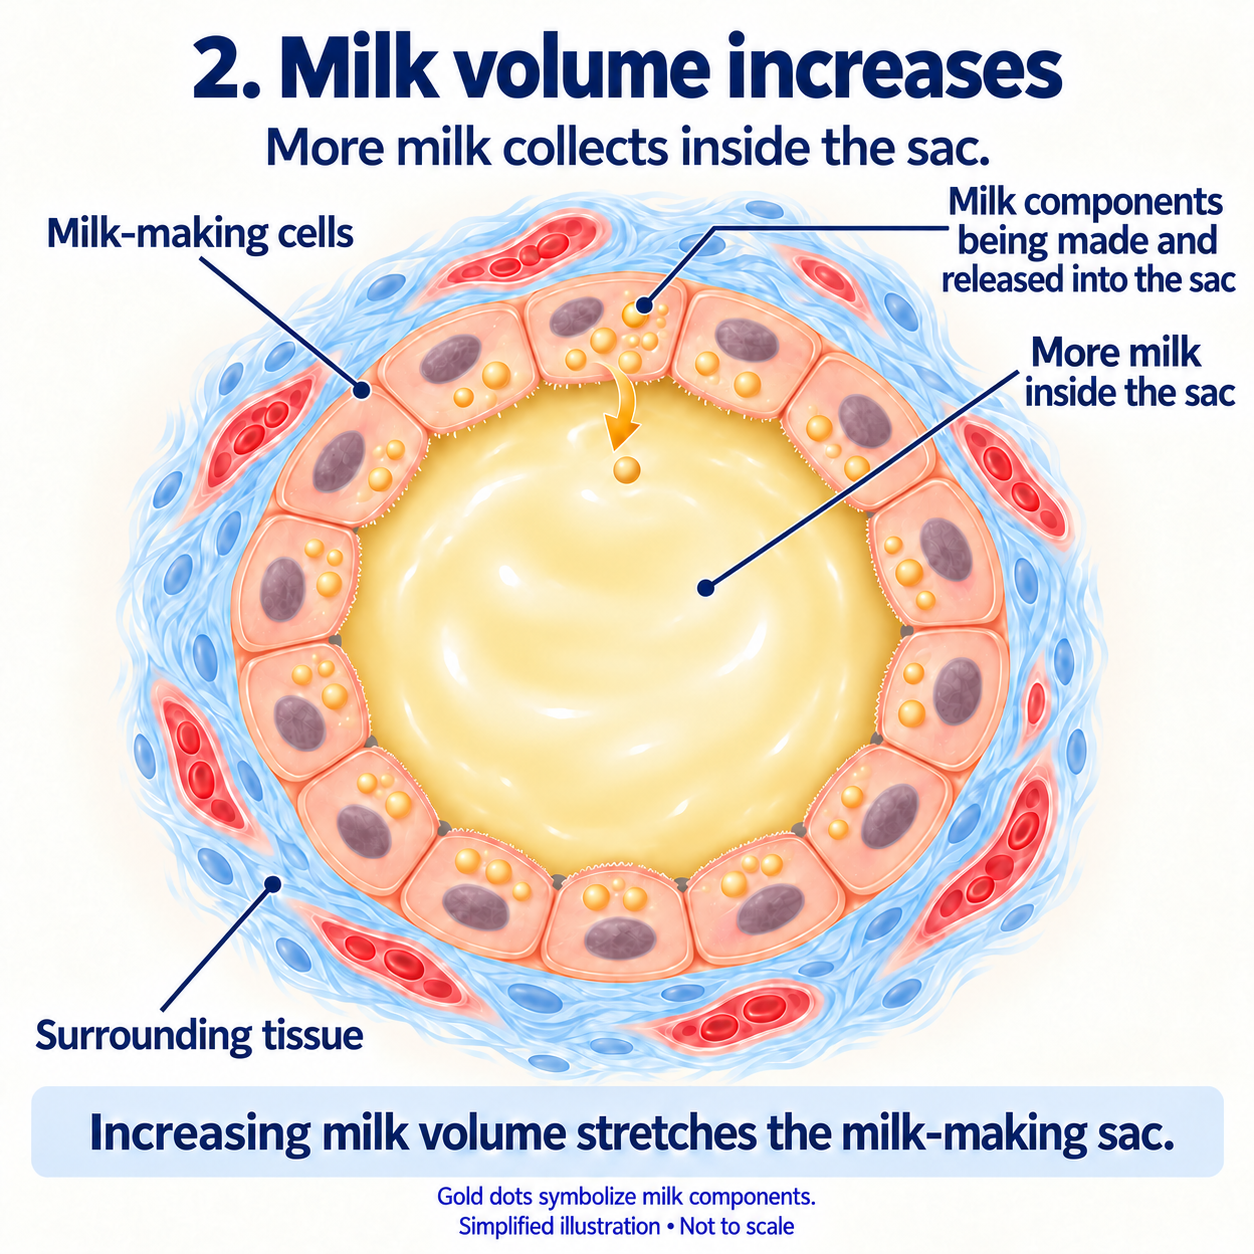
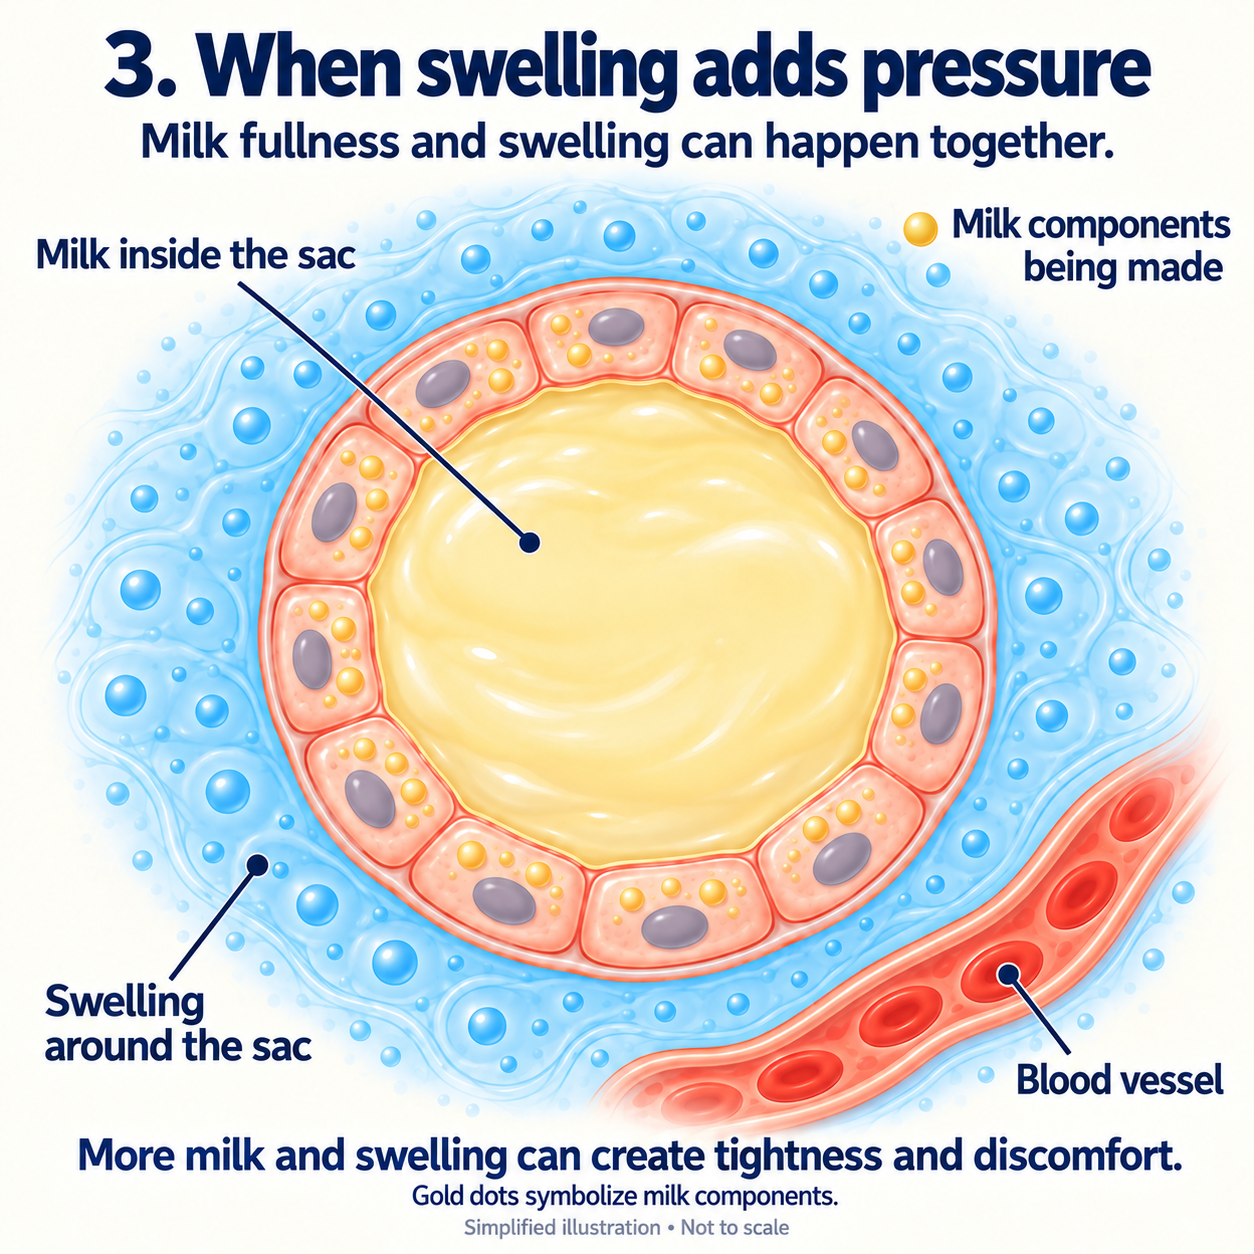
These are simplified illustrations, not pictures of the exact size or pressure inside your breast. Tap or click any image to see it larger.
If you received IV fluids during labor, extra tissue swelling may add to the discomfort. A small observational study found more breast swelling among parents who received IV fluids, although it couldn’t establish that the fluids caused it. That extra swelling may help explain why your breasts still feel firm after milk has been removed.
The good news is that early postpartum swelling is usually temporary.
Feeding your baby or expressing milk when needed can relieve milk pressure while the swelling settles. Your breasts may still feel firm afterward because removing milk doesn’t directly remove fluid from the surrounding tissue.
Why is it Important to Manage Engorgement?
Milk can gradually accumulate between feeds, adding pressure as the sacs fill. If the areola—the darker area around your nipple—becomes tight and swollen, your baby may have trouble getting a comfortable mouthful of breast tissue. If feeding becomes less effective, more milk can remain behind and add to the fullness.
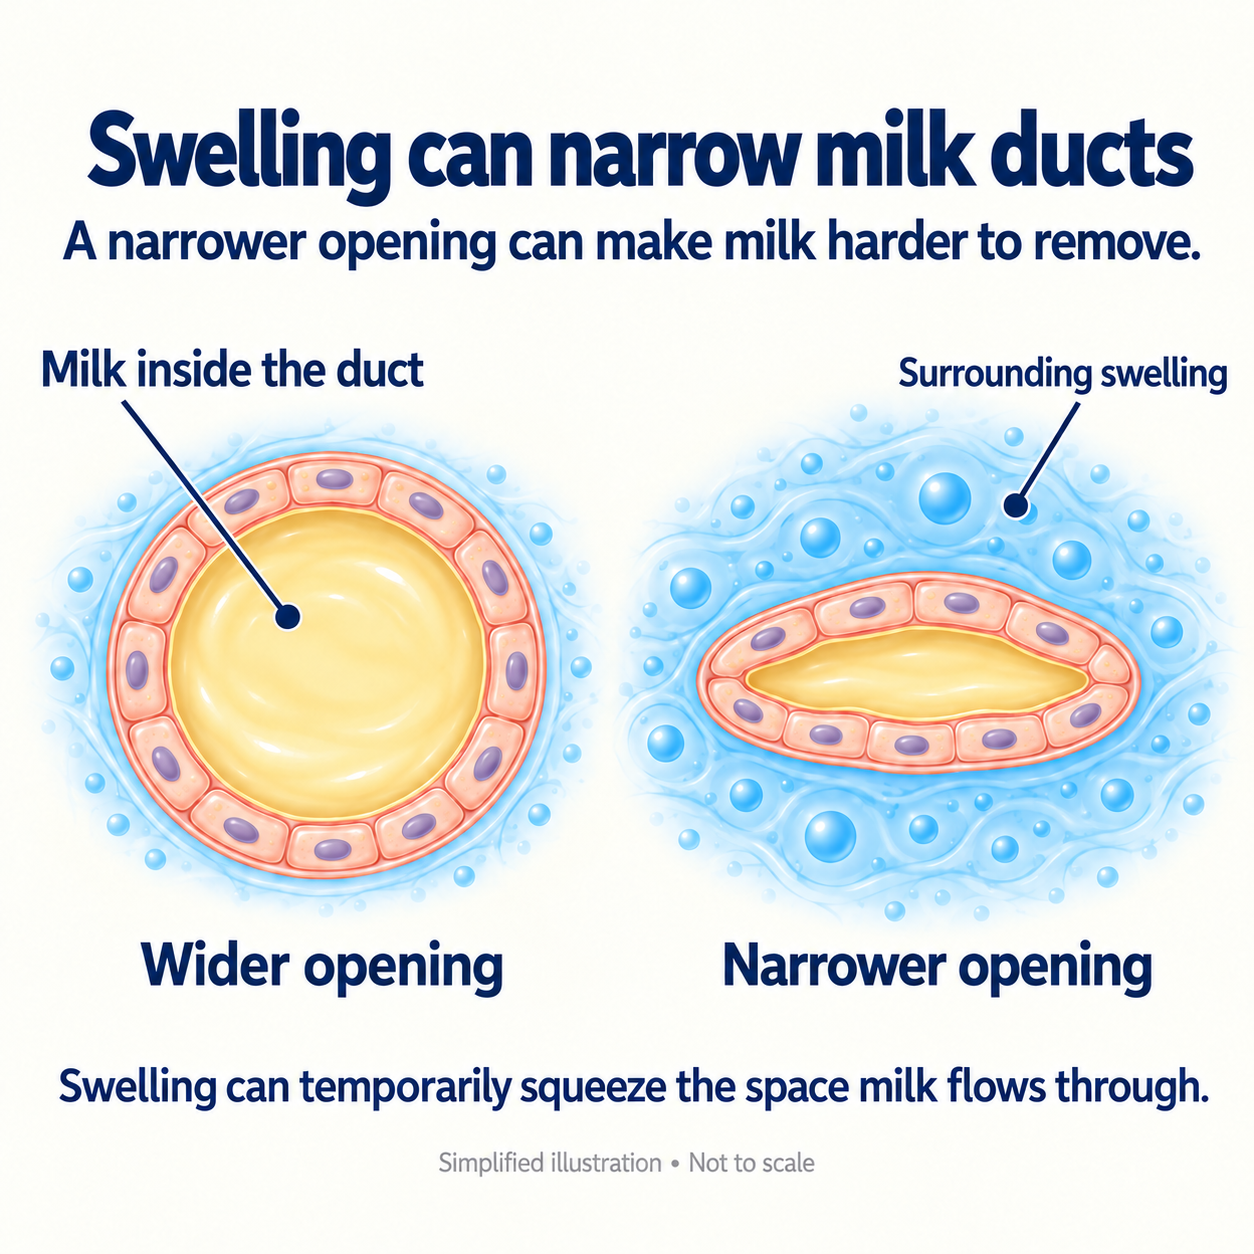
Swelling can also put pressure on milk ducts, narrowing the space milk flows through. That can make getting milk out harder, even when your breasts feel incredibly full.
This is the cycle we want to interrupt: fullness and swelling make feeding harder, and difficulty removing milk can add to the pressure.
We need to help milk move while also helping the swollen tissue settle.
You don’t have to wait for all the swelling to disappear before feeding, and you don’t need to keep pumping until every bit of firmness is gone.
How to Relieve Engorgement
Start with what is getting in the way right now. Frequent, comfortable milk removal matters, but a baby who cannot latch onto a swollen areola may need help getting started.
1. Keep Milk Moving From the Beginning
Most newborns feed 8–12 times in 24 hours, often more. Many babies will naturally ask to feed this often when you keep them close and respond to their early feeding cues. Offer the breast when they begin rooting, moving their hands toward their mouth, or becoming restless, rather than waiting until they are crying.
If your baby is especially sleepy after birth, one simple place to start is to unwrap the swaddle and spend time skin-to-skin. Hold your baby wearing just a diaper against your bare chest, with a light covering over their back for warmth and their face uncovered. This gives them room to move and can help encourage their natural feeding behaviors.
Swaddling can help some babies stay asleep longer. If your newborn is already sleeping through opportunities to feed, unwrapping them is a useful first step when encouraging them to wake. Skin-to-skin can help, but if your baby isn’t waking to feed regularly, ask your maternity team about waking them and offering feeds, commonly every two to three hours while feeding is being established.
You need rest, too. A partner or another trusted adult can hold your baby skin-to-skin between feeds while you take a nap, then bring your baby back when they begin showing feeding cues. The person holding your baby needs to stay awake and alert, with your baby’s face visible and nose and mouth clear. If they become sleepy, your baby should move to a separate, firm, flat sleep space on their back.
Frequent feeds only help if your baby is actually removing milk. If they repeatedly slip off, feeding hurts, or they fall asleep before feeding effectively, ask for help. These signs that your newborn is getting enough milk can help you know what to watch for.
2. Soften the Areola Before Latching
When the area around your nipple feels tight and swollen, reverse pressure softening can make it easier for your baby to attach. It temporarily shifts some tissue fluid away from the area they need to latch onto. It doesn’t drain the whole breast or squeeze milk out.
With clean hands, place your fingertips around the base of your nipple. Apply gentle, steady pressure straight back toward your chest wall for about a minute, without causing pain.
This gently shifts some fluid away from the area around your nipple, making the tissue easier for your baby to latch onto.
Reposition your fingers if needed and repeat until the area feels softer. Offer the breast or express soon afterward, while the tissue is easier to shape.
An IBCLC or postpartum nurse can demonstrate the technique. You can also follow the HSE’s illustrated reverse pressure softening guide.
Once the areola is softer, this step-by-step latching guide can help you position your baby for a more comfortable feed.
3. Use Light Touch, Not Deep Tissue Massage
When your breasts feel hard, it can be tempting to massage harder to get things moving. But swollen breast tissue needs gentle handling. Deep kneading, digging into a hard area, or forcefully pushing toward the nipple can injure tissue and worsen swelling.
Very light strokes over the skin toward your armpit or upper chest may help fluid movement and ease discomfort. Think of gently stroking the skin, rather than pressing into the tissue underneath.
In a small randomized trial involving 67 postpartum participants, manual lymphatic drainage added to routine breast care improved pain and engorgement more than routine care alone. That is encouraging, although it doesn’t establish one ideal technique for everyone.
You can also try gentle breast movement, sometimes called breast gymnastics. Maya Bolman, IBCLC, demonstrates breast gymnastics here. Support and gently move the breast rather than kneading or squeezing it.
This is an optional comfort technique; the lymphatic drainage study did not test breast gymnastics itself. Stop if it hurts.
4. Express Milk When Needed
If your baby is feeding effectively but your breasts remain uncomfortably full, hand express a little milk to ease pressure.
A small amount before feeding may also help soften the breast for latching. You can stop when you feel more comfortable rather than trying to make your breasts completely “empty.”
If your baby cannot latch or is not transferring enough milk, expressing just a little for comfort may not be enough.
You need a plan to feed your baby and replace the milk removal they are missing. Hand expression, pumping, or a combination may be useful, depending on your situation. Get support promptly rather than continuing through missed feeds.
Necessary milk removal is not something you need to avoid out of fear of oversupply. At the same time, repeatedly pumping beyond your baby’s needs can encourage more production. How Milk Supply Actually Works explains that relationship.
If a pump is needed, use comfortable suction and a suitable flange fit; higher suction is not a solution to swollen tissue - it just increases the potential for more damage.
5. Use Cold for Comfort and Swelling
A cool compress or cold pack wrapped in a thin cloth can help relieve pain and swelling between feeds. Try about 10 minutes at a time, checking your skin and stopping if it becomes uncomfortable. Don’t put ice directly against your skin.
If a little warmth feels soothing or helps milk begin flowing, use a comfortably warm cloth briefly before feeding or expressing.
Prolonged or intense heat can worsen swelling, so you don’t need a long heat treatment or a routine of alternating hot and cold compresses.
6. Support Your Comfort While Things Settle
A comfortable, supportive bra may help, as long as it isn’t tight or pressing into tender tissue.
Ibuprofen can help with pain and inflammation, and acetaminophen can help with pain. Both are commonly used during breastfeeding.
Follow the label or your clinician’s instructions, and check with your healthcare professional if you have a condition or take medicines that could make either unsuitable.
When to Reach Out for Help
If your baby cannot latch or you are unsure they are getting enough milk, get help promptly.
You don’t need to wait two or three days for engorgement to resolve. An IBCLC can watch a feed, help soften the areola, assess milk transfer, and work with your care team on a feeding plan.
Contact your baby’s healthcare provider if they have fewer wet diapers than expected for their age, increasing yellowing of the skin, or persistent sleepiness that interferes with feeding.
A baby who is difficult to wake or too weak to feed needs urgent medical assessment.
Engorgement itself is not an infection, although a slight temperature rise can occur. A fever does not automatically mean bacterial mastitis, but it should not be dismissed as “milk fever.”
Seek medical care promptly for a temperature of 100.4°F (38°C) or higher, chills, feeling unwell, worsening breast redness or discoloration, or increasing pain. Fever after childbirth can have causes beyond the breast. Bacterial mastitis may need antibiotics; engorgement alone does not.
If you feel well but the swelling isn’t beginning to improve within a day or two, or keeps returning, ask for an assessment. Your comfort matters, even when your baby appears to be getting enough milk.
Final Thoughts:
Early engorgement is a combination of milk fullness and changes in the surrounding tissue. That’s why the most useful approach addresses both: help your baby feed frequently and effectively, soften a swollen areola when needed, and give tender tissue gentle care while the swelling settles.
You don’t have to force milk out or handle this alone. Start with the next feed, ask someone to help you rest between feeds, and reach out early if feeding isn’t working. You and your baby both deserve support.
Sources — click to open
- ACOG: Breastfeeding Challenges — engorgement, tissue edema, and milk expression
- Academy of Breastfeeding Medicine: Clinical Protocol #36 (2022) — postpartum engorgement and gentle breast care
- Ramsay and colleagues (2005): Anatomy of the lactating human breast redefined with ultrasound imaging — primary study of duct anatomy and compressibility
- Kujawa-Myles and colleagues (2015): Maternal intravenous fluids and postpartum breast changes — pilot observational study
- NHS: Breastfeeding in the first few days — feeding frequency and early cues
- UNICEF UK Baby Friendly Initiative: Skin-to-skin contact — feeding behaviors and safe positioning
- Franco and colleagues (2005): Influence of swaddling on sleep and arousal — sleep study in infants aged 6–16 weeks, not an engorgement study
- South Tees Hospitals NHS Foundation Trust: Skin-to-skin safety — alert caregivers and airway positioning
- Cotterman (2004): Reverse pressure softening — original clinical technique report
- HSE: Reverse pressure softening — illustrated instructions
- Doğan, Eroğlu, and Akbayrak (2021): Manual lymphatic drainage, kinesio taping, and routine care for breast engorgement — randomized trial
- Maya Bolman, IBCLC: Breast Gymnastics — technique demonstration, not a clinical trial
- HSE: Engorgement while breastfeeding — relief, pain medicines, and when to get help
- CDC: Urgent Maternal Warning Signs and Symptoms — fever after childbirth
Images in this blog were AI-generated.
Want More Support?
If this blog was helpful, here are a few related resources you might like.
➜ Establishing Your Milk Supply: What to Know in the First Two Weeks
➜ Signs Your Breastfed Baby Is Getting Enough Milk
🔒 Go Deeper: Understanding Low Supply
🔒 Expanded Access includes step-by-step videos and resources that go beyond the blog to help you understand and work through common feeding challenges.
Frequently Asked Questions


